
Testosterone prescriptions for older American men more than tripled in a decade, and the therapy market grew to $1.6 billion a year. You’ve seen the ads: tired, low drive, one quick fix. What the ads don’t mention is the fine print, the regular bloodwork, the fertility hit, an FDA clot warning, and active litigation against five of the manufacturers. So when guys ask what are the cons of TRT for men, the honest answer is longer than a side-effect list. Some cons show up in week one, some bill you every month, some may be permanent, and some nobody can measure yet because the therapy is measured in decades, not weeks.
This piece lays out every documented downside, organized by when it actually shows up in your life, and explains why the heart-risk evidence genuinely conflicts instead of pretending it doesn’t. It’s not a scare piece. It’s also not a clinic ad. It’s the trade-off sheet the marketing skips.
Key Takeaways
TRT costs roughly $1,650 to $3,200 per year and requires recurring bloodwork and doctor visits for as long as you’re on it, which is likely decades.
The heart-risk evidence genuinely conflicts: a 25,420-man Medicare study found no increased heart attack risk, while a VA study of 8,700 angiography patients found nearly 26% on TRT had a stroke or heart attack versus 20% off it.
TRT suppresses sperm production, so if kids are even a maybe, fertility preservation needs to be discussed before the first injection, not after.
Table of Contents
What TRT is, and what it was originally approved for
TRT is a medical treatment for clinically low testosterone, called hypogonadism, delivered as gels, injections, skin patches, pellet patches, or implants under the skin. Testosterone governs sperm production, bone density, fat distribution, muscle strength, sex drive, and red blood cell production, so messing with it touches a lot of systems at once.
It was first approved for men with little to no testosterone. Klinefelter’s disease or removal of both testicles, and the approval was based on normalizing blood levels, not symptom relief. That gap between what it was approved for and how it’s marketed now quietly reframes the whole decision.
Does TRT increase the risk of heart attack and stroke?
Neither “heart-safe” nor “heart-dangerous” is a supportable answer, and the disagreement is about methods, not a hidden truth. Two large studies looked at the same question and landed on opposite sides, and the reason they disagree tells you more than either number alone.
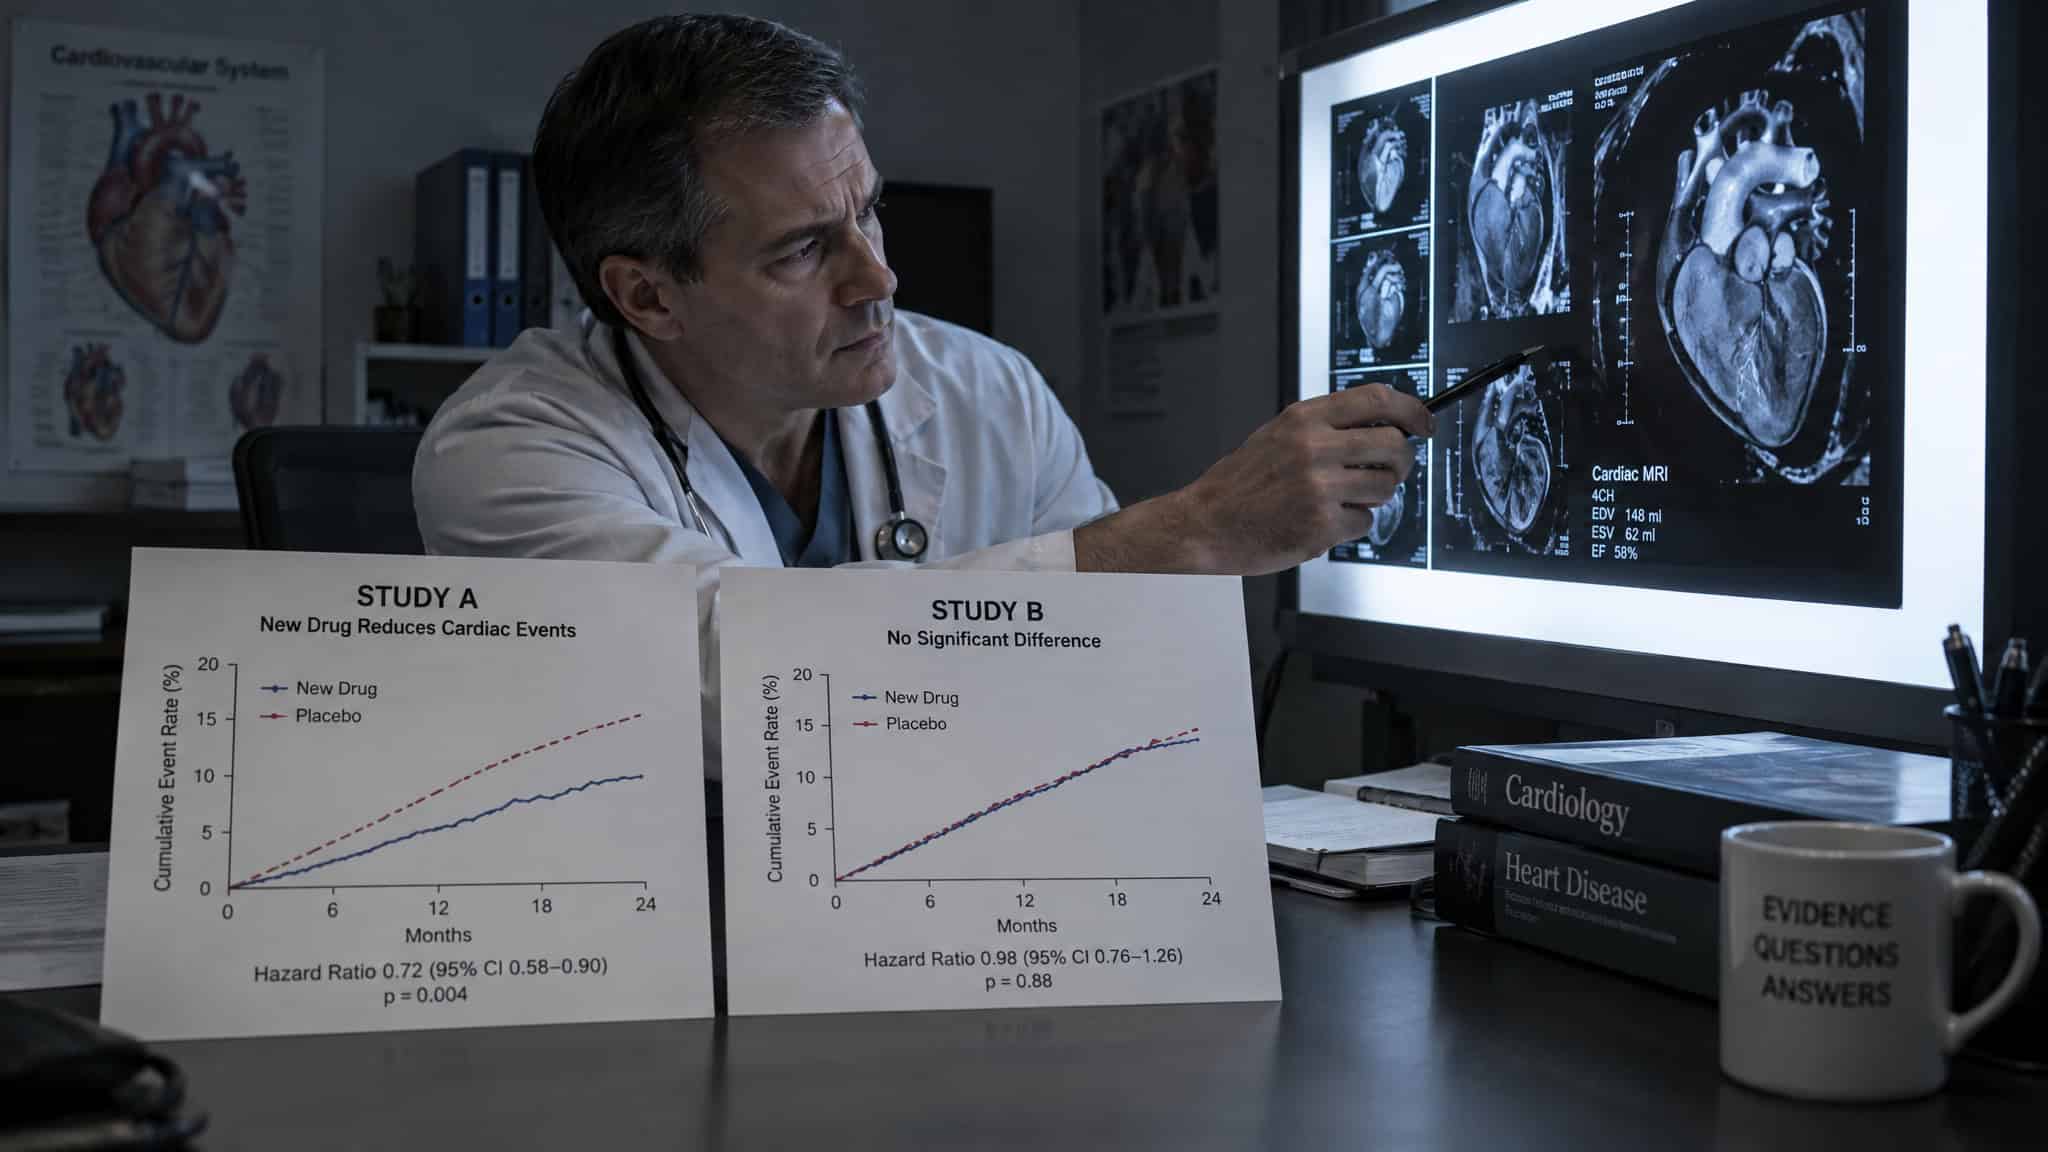
The reassuring side: a University of Texas Medical Branch team studied 25,420 Medicare beneficiaries aged 66 and older, treated for up to eight years between 1997 and 2005, with controls matched on age, race, Medicaid eligibility, and health status. No increased heart attack risk. The kicker that makes the debate confusing: users with higher cardiovascular probability actually had a lower heart attack rate than equivalent non-users. It was government-funded through the NIH and AHRQ, not drug-company money, and published in Annals of Pharmacotherapy.
The lead author’s own caveat is worth keeping: large randomized trials will provide more definitive evidence. That’s not “TRT is proven safe.”
The other side: a JAMA-linked VA study co-authored by Dr. Michael Ho, drawing on data from the Veterans Affairs Eastern Colorado health care system, reviewed 8,700 men in their early 60s, all of whom had coronary angiography between 2005 and 2011 and all had low testosterone. About 1,200 started therapy roughly a year after testing. Nearly 26% of men on therapy had a stroke or heart attack versus 20% off it. Dr. Laurence Klotz of Sunnybrook says the findings confirm real safety concerns.
Why they disagree: the VA population was already high-risk men getting heart imaging, and the study was observational. The UTMB study, by contrast, followed 25,420 Medicare beneficiaries aged 66+ treated for up to eight years and found no increased heart attack risk, with controls matched on age, race, Medicaid eligibility, and health status. The randomized TRAVERSE trial sits in between. One review in Therapeutic Advances in Drug Safety found no conclusive evidence of harm with prolonged use; other studies point to increased cardiovascular risk; critics have questioned the quality of some of the risk data; and everyone agrees more research is needed. That’s the rare point of consensus.
The risks that survived the best evidence: clots, AFib, kidney injury, blood pressure
Yes, TRT carries a documented risk of blood clots in the veins. That’s not speculation, it’s an FDA labeling warning, decided June 20, when the agency expanded testosterone product labels with a general venous clot warning. The FDA and the European Medicines Agency are still examining testosterone safety, so nobody has fully closed the book.
The newest good evidence still found real downsides. TRAVERSE, an industry-sponsored randomized trial, credit where due, found no elevated cardiovascular or prostate disease risk overall. But the TRT group had higher risks than placebo of blood clots in the lungs, atrial fibrillation, and acute kidney injury. Those three signals prompted FDA labeling changes.
The regulatory arc reads like a trade, not a reversal. In 2014, the FDA warned of reports linking TRT to higher risk of stroke, heart attack, and death, and urged extra caution for men with prostate cancer or an enlarged prostate. Later, the FDA proposed removing the heart attack and stroke label language, dropping the “unproven in age-related hypogonadosis” language, and adding a new warning about treatment-related blood pressure increases. The honest read: the risk didn’t vanish, it moved. The regulator traded one risk set for a more specific one, and, as Marc Garnick has framed it, is easing access and prescriber hesitancy at the same time.
One more piece of context for why skepticism about the industry is fair: Abbott Laboratories, AbbVie Inc., Eli Lilly, Pfizer, and Actavis face consolidated multidistrict litigation in Federal Court over claims they hid treatment risks. Claims, not findings. But it’s a $1.6 billion market, and the litigation record explains why some guys read the ads with a raised eyebrow.
TRT side effects: the full list, what causes them, and who shouldn’t take it
TRT side effects include acne, enlarged prostate, fluid retention, sleep apnea, breast enlargement, swollen ankles, smaller testicles, thickened blood (erythrocytosis), bladder irritability, and in some cases heart attack and other cardiovascular complications. Here’s the full inventory, sorted by what actually happens to you, with the mechanism where it’s known.
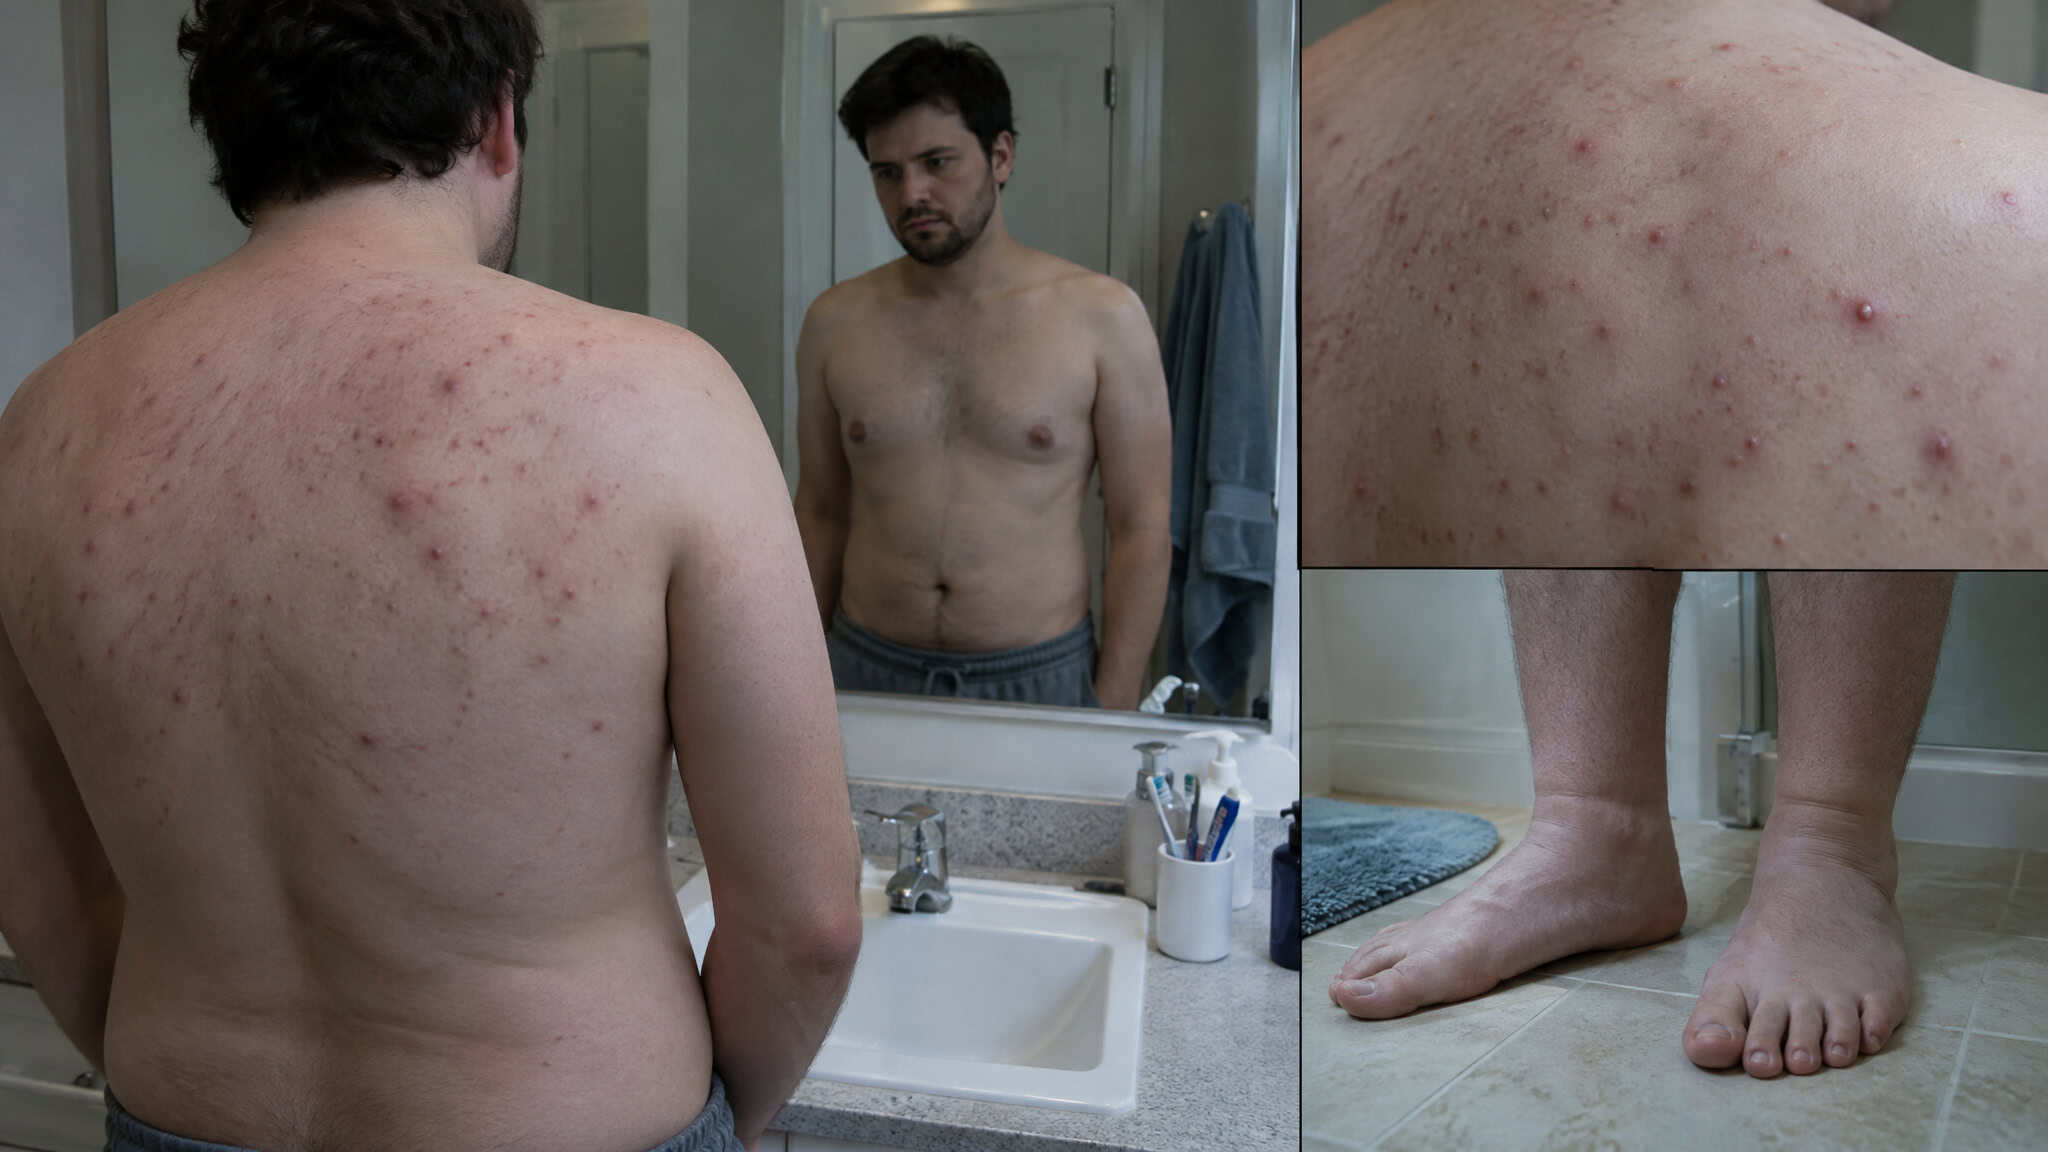
The everyday stuff:
- Acne. The mundane one. Guys on TRT talk about back acne like a rite of passage. Annoying, real, not dangerous.
- Fluid retention and swollen ankles. More testosterone can mean an enlarged prostate, and an enlarged prostate can mean more swelling. The daily-life version: your socks leave marks by evening.
- Bladder irritability, mood changes, and cholesterol changes. Less dramatic, still on the list.
The ones worth taking seriously:
- Sleep apnea can show up or worsen. If you snore like a chainsaw, that’s worth checking before you start, not after.
- Breast enlargement. Said straight: it happens, through hormone conversion. Guys deserve to know before the pharmacy tells them.
- Smaller testicles. When you’re supplying testosterone from outside, your natural production shuts down, and the equipment follows. Blunt, unembarrassed. You’re grown.
- Erythrocytosis. This is the mechanism con behind half the list. Excess testosterone tells your bone marrow to overproduce red blood cells, the blood gets thicker, and stroke risk climbs. The same excess can promote prostate growth, per the Mayo Clinic’s explanation. This is exactly why the bloodwork exists, which we’ll get to below.
And the serious end: heart attack and cardiovascular complications remain on the list, which is why the evidence fight above matters.
Conditions that make TRT risky outright. Some guys shouldn’t touch this, and it’s worth knowing if you’re one of them before you’re emotionally invested: breast cancer (men get it too, and it changes the math completely), prostate cancer, heart disease, prior stroke, and untreated sleep apnea, a big part of who genuinely is a candidate versus who isn’t. That last one has a useful distinction: untreated apnea is the problem. Treated apnea is a different story.
“Safer than steroids” is not “safe.” Supervised replacement still carries this whole list. Supraphysiologic steroid abuse adds the thickened-blood-and-stroke mechanism on top. The decisive difference is dose and medical supervision, not risk-free versus risky.
TRT and the prostate: tiered risk, not a binary warning
Yes, TRT affects the prostate, but the risk is tiered, not binary, and the decisive factors are what your prostate is doing and how old you are. Dr. Heidi Rayala’s point explains the whole concern in six words: prostate growth is testosterone-dependent.
Tier 1: metastatic prostate cancer. Off the table, full stop. If it’s spread, this isn’t your treatment.
Tier 2: low-grade, localized, known or suspected cancer. A softer warning and a physician conversation, not an automatic no. Garnick’s threshold: men five or more years past localized therapy with no recurrence may possibly take TRT safely. Both hedges matter, because the data aren’t from randomized trials.
Tier 3: BPH, the enlarged prostate. Mild to moderate symptoms, TRT is still on the table. Severe symptoms, skip it. The awkward irony worth naming: some BPH treatments can themselves impair sexual function, so the fix for one problem can cause the other.
Now the time-horizon con, which is the one a 35-year-old should sit with. TRAVERSE found that urinary symptoms did not worsen among men with mild to moderate BPH, but it followed those men for less than three years. Nobody knows how a younger man’s prostate fares over decades, because that data doesn’t exist yet. The honest question is is it a good idea to start TRT at age 36? A real consult weighs your age, symptom severity, family history, how long you’d likely stay on therapy, and what you want sexually.
The counterintuitive con: testosterone nudges PSA up a little, so not every bump is bad news. But rising PSA on testosterone replacement therapy has led, in Garnick’s own practice, to diagnoses of likely pre-existing prostate cancer in men referred to him. The monitoring actually earns its keep.
Fertility: the decision that has to happen before your first injection
TRT suppresses sperm production and quality. Flat statement, and the ordering is the whole point: this gets decided before your first injection, not after.

The mechanism is the same shutdown that shrinks your testicles. Exogenous testosterone suppresses the testicles’ own production, so sperm count and quality drop with it. It’s mechanistic, not incidental, which means “I’ll worry about it later” isn’t a plan.
The common sequencing mistake looks like this: a guy in his 30s starts TRT for energy and libido, feels great, and only later learns that the treatment shutting down his natural testosterone production also shut down his sperm production. A basic grasp of what testosterone does in the male body makes the stakes clearer here: if kids are even a maybe, fertility preservation options get discussed with a doctor before starting. That’s exactly the sequencing the marketing skips.
Buyer rule: If kids are even a maybe, discuss fertility preservation with a doctor before your first injection, not after.
One honest limitation: the evidence here doesn’t establish whether or how fast fertility recovers after stopping. Nobody should promise you a timeline, because there isn’t one to promise.
What TRT actually costs and demands: money, bloodwork, and slow results
TRT costs roughly $1,650 to $3,200 per year, and the range varies by insurance coverage, location, medical fees, medication type, administration mode, and dosage. Prices may vary, so treat the range as a planning number, not a quote.
What does the number buy? Medication, doctor visits, and lab tests. That last part matters because guys budget for the vial and forget the blood draws. Your mileage will vary depending on:
- Insurance coverage. The single biggest swing factor.
- Where you live and what your doctor charges. Clinic fees differ a lot by region.
- Medication type, administration mode, and dose. A daily gel and a weekly injection don’t cost the same, and neither does a pellet implant.
Blood tests and doctor visits for as long as you’re on it. This is the underrated con: it’s a commitment, not a one-time fix. Recurring bloodwork (hematocrit, PSA, red blood cell counts), follow-up appointments, and dose adjustments become routine for as long as you’re on therapy. Garnick’s protocol is a good picture of what “monitoring” means in practice: rule out underlying clotting issues before starting, which is cheap insurance before you commit; regular hemoglobin and hematocrit checks to avoid circulatory problems; and routine PSA and red cell counts for everyone. Worth knowing why the PSA checks matter: testosterone can cause small PSA elevations, and that uptick sometimes leads to a diagnosis of prostate cancer that was already there.
Some men find their hematocrit creeps up over time and need a dose reduction. None of this is scary. It’s the price of admission, part of the deal. Think of it less like a purchase and more like a subscription you can’t easily cancel.
Delivery methods: gels vs injections vs patches vs pellets vs implants. TRT is administered as gels, injections, skin patches, pellet patches, or subcutaneous implants. Each gets testosterone into your body differently, with a different daily burden and side-effect profile:
| Method | Daily burden | Key trade-off |
|---|---|---|
| Gels | Daily application | Steady, but transfer and daily routine |
| Injections | Periodic, self-administered | Less frequent, but needles and level swings |
| Skin patches | Daily | Simple, skin irritation possible |
| Pellet patches | Periodic placement | Low daily effort |
| Subcutaneous implants | Occasional procedure | Can’t easily take it back once in |
That last row is the trade-off worth naming: pellets and implants are low-maintenance precisely because they’re in there, and if something goes sideways, you can’t just skip tomorrow’s dose.
Slow, uneven results. Worth knowing the calendar so you don’t quit at week eight: fatigue lifts within 3 to 4 weeks, depression relief is possible within 6 weeks (possible is doing work there), sex drive returns within 3 to 6 weeks, and stronger erections plus bone benefits take about 6 months. It’s a calendar, not a promise.
Is your “low T” even low? The overdiagnosis con
Here’s a con of the TRT ecosystem itself: the Mayo Clinic points out that low-T advertising targets symptoms that could apply to most American men, while truly low testosterone affects only a small fraction, and no exact figure exists. The legitimate diagnostic bar is two separate morning testosterone values below 300 ng/dL plus real symptoms: decreased libido, fewer spontaneous erections, fatigue, low energy, depressed mood. Normal range is 300 to 1,000 ng/dL. Feeling tired at 45 isn’t a diagnosis. A common pattern in low-T clinics: one afternoon blood draw after a bad week of sleep, same-week prescription, the two-morning standard never mentioned.
Red flag: One afternoon blood draw plus a same-week prescription skips the two-morning diagnostic standard entirely.
Is it bad to be on TRT for life? The honest counterweight
No, being on TRT for life is not inherently bad, but no evidence establishes a safe duration, and the decades-long tail of risks is genuinely unmeasured. No source supports a specific number of years. TRAVERSE’s follow-up limits and the FDA’s own shift, dropping the “unproven in age-related hypogonadism” language, mean the evidence supports “long-term unknown,” not a verdict.
There are boundaries worth holding. TRT isn’t for treating normal aging absent an underlying medical condition, and it doesn’t replace diet, exercise, and stress management. The shot doesn’t cancel the couch. Garnick suspects fewer men than expected will see the dramatic improvement they’re promised; effects vary person to person.
The testimony goes both ways. Dr. Larry Komer of the Masters Men’s Clinic, who has treated roughly 4,000 men, says patients call therapy “life changing,” with restored marriages and happiness. Gary Rodger, 50, reports restored libido, calmness, and what he calls a “zest for life,” and refuses to stop despite the risk evidence. That’s one man’s experience, not data, but for some guys the felt benefit outweighs the published risk, and that’s a real trade-off.
The counterweight: Dr. Laurence Klotz says the VA study confirms his longstanding safety concerns. Komer’s position, that therapy can be safe when individually tailored, is the reasonable middle. Attribute it, don’t take it as a guarantee.
Try the modifiable causes first: lifestyle alternatives before therapy
For a lot of men, the strongest con of starting TRT is that a modifiable cause, weight, sleep, stress, was never addressed first. These are worth trying first because they’re cheap or free, not because you need to earn your testosterone.
About 30% of obese men run lower testosterone than healthy-weight men, and resistance training stimulates production, with exercise beating weight loss alone for this. Good news if you already lift. Sleep is the cheapest intervention on the list: University of Chicago research shows insufficient sleep lowers testosterone, and 7 to 8 hours is the target. Chronic stress raises cortisol, which drags testosterone down. One cause, one effect, no coaching required.
Supplements, vitamin D, DHEA (dehydroepiandrosterone), zinc, magnesium, ashwagandha, fenugreek, have some evidence behind them but work best in men who are actually deficient, and none substitute for the fundamentals. A diet with enough zinc, vitamin D, and omega-3s supports production. Boring but true.
So the decision path, stated directly: if your symptoms are real and confirmed by two morning readings, discuss the full cons picture with a physician. If they’re not, the lifestyle path is the cheaper, lower-risk first move.
Frequently Asked Questions
How long can a man stay on TRT?
There’s no established maximum — therapy typically continues for as long as you and your doctor decide the benefits outweigh the risks, which for most men means years or decades. The honest limitation is that no source supports a specific safe number of years, because the therapy’s long-term risks are measured in decades that the research hasn’t covered yet.
What are the disadvantages of testosterone replacement therapy for men?
The documented downsides include acne, fluid retention, sleep apnea worsening, breast enlargement, smaller testicles, thickened blood (erythrocytosis), prostate effects, suppressed fertility, an FDA clot warning, and recurring bloodwork and costs of roughly $1,650 to $3,200 a year. Some cons show up in week one, some bill you monthly, some may be permanent, and the decades-long risks can’t be measured yet.

